Articles Tagged with

hypnotherapy london

Home / hypnotherapy london
Nervous System
Health

Nervous System Regulation: What It Means and How Hypnotherapy Helps

“Nervous system regulation” has become one of those phrases you hear everywhere, from therapy rooms to social media. It is a useful idea, but it often gets explained vaguely. In this article I want to set out clearly what your nervous system is, what it does in your body, what happens when it stays stuck in a stressed state, and why hypnotherapy is one of the more direct ways of helping it settle. I will also be honest about what the research does and does not show.
Nervous System

What Is the Nervous System?

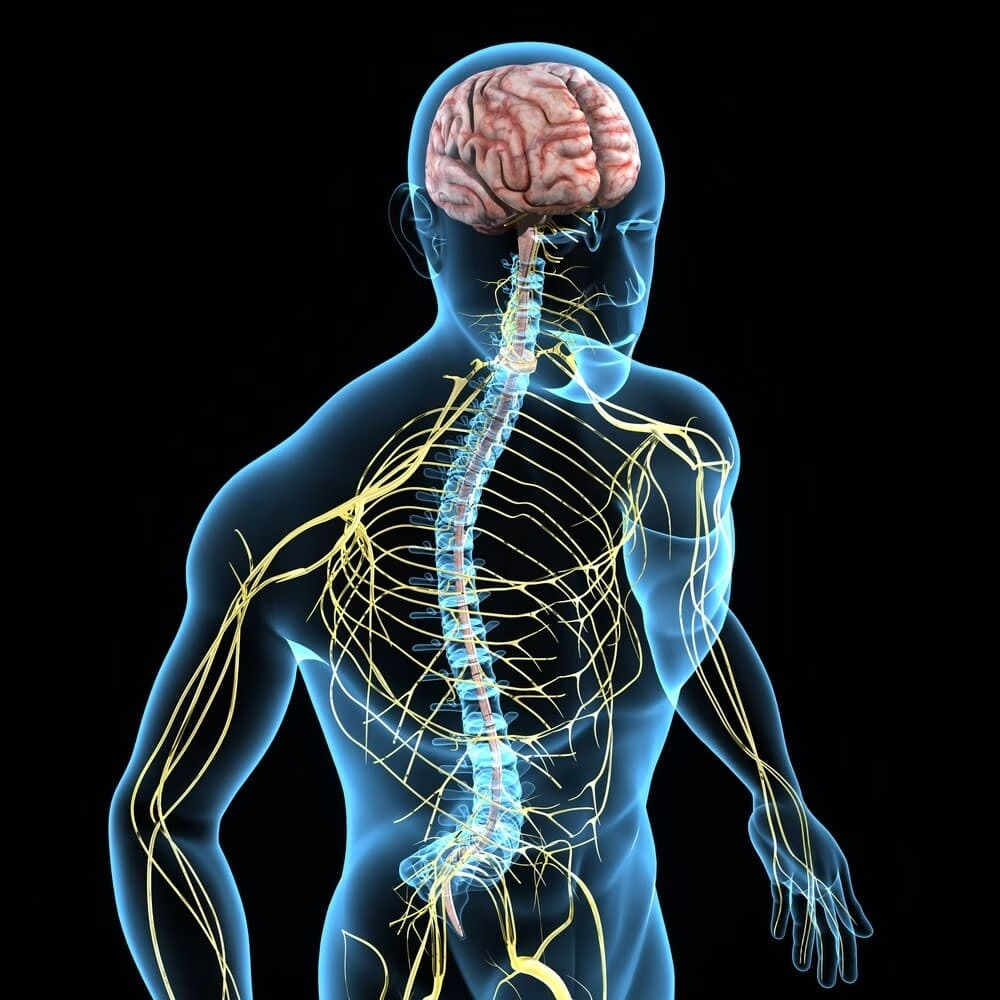
Your nervous system is the body’s communication network. It has two main parts:

  • The central nervous system: your brain and spinal cord, which take in information, make sense of it and decide how to respond.
  • The peripheral nervous system: the nerves that carry messages between the brain and the rest of the body, including your muscles, skin and internal organs.

When people talk about “regulating” the nervous system, they usually mean one particular branch of it: the autonomic nervous system. This is the part that runs automatically, without you having to think about it. It controls your heart rate, breathing, blood pressure, digestion, sweating, muscle tension and much more.

What the Autonomic Nervous System Does in Your Body

The autonomic nervous system has two main branches that work together, a little like an accelerator and a brake.

The sympathetic branch (the accelerator). This prepares you for action. When you sense a threat or a challenge, it raises your heart rate, speeds up your breathing, tenses your muscles, sharpens your attention and sends blood away from digestion towards your limbs. Alongside it, the body releases stress hormones such as adrenaline and cortisol. This is the familiar “fight or flight” response.

The parasympathetic branch (the brake). This helps you rest, recover and digest. It slows the heart, deepens and steadies breathing, supports digestion and allows the body to repair itself. Much of this work is carried out by the vagus nerve, a long nerve running from the brainstem to the heart, lungs and gut.

Neither branch is “good” or “bad”. A healthy nervous system is a flexible one. It speeds up when you need energy, for a presentation, a run or a difficult conversation, and then returns to a calmer baseline when the moment has passed. That ability to shift up and come back down is what regulation really means.

One common way researchers measure this flexibility is heart rate variability (HRV), the natural variation in time between heartbeats. Higher HRV at rest generally reflects stronger parasympathetic activity and a more adaptable system. Lower HRV is associated with chronic stress and a range of health problems.

What Happens When the Nervous System Is Not Regulated?

The stress response is designed to be short-lived. Problems start when it is switched on too often, too strongly, or for too long, and the body does not get the chance to return to baseline. The neuroscientist Bruce McEwen described this cumulative wear and tear as “allostatic load”: the same stress systems that protect us in the short term can contribute to damage when they are overused over months and years (McEwen, 1998).

Prolonged activation of the stress system has been linked with a wide range of problems, including anxiety and low mood, disturbed sleep, digestive difficulties, raised blood pressure, and changes in immune function (Chrousos, 2009). In everyday life, a dysregulated nervous system often shows up as:

  • Feeling “on” all the time: restless, irritable, easily startled, unable to switch off in the evening.
  • Sleep problems: lying awake with a racing mind, or waking at 3am with your heart pounding.
  • Gut symptoms: the gut is closely wired to the nervous system, which is why stress so often shows up as bloating, pain, urgency or constipation. I have written more about this in my article on the gut-brain axis.
  • Physical tension: tight jaw, shoulders or chest, headaches, shallow breathing.
  • Anxiety and panic: the body reacting as if there is danger when, logically, there is not.
  • Shutdown and exhaustion: for some people the opposite happens. After a long period of stress they feel flat, numb, foggy and depleted, which is often what burnout feels like from the inside.

You may have come across polyvagal theory, developed by Stephen Porges, which describes these states in terms of safety, “fight or flight” and “shutdown” (Porges, 2007). Many therapists find it a helpful way to talk about how the body responds to stress. It is worth knowing, though, that several of its specific biological claims have been strongly questioned by other researchers (Grossman, 2023). I use it as a useful map for clients rather than as settled science. The underlying point is well supported: the body’s stress systems can become stuck, and that affects how you feel physically and emotionally.

Why You Cannot Simply “Think” Your Way Calm

Most people I see already know they are stressed. They have been told to relax, and many have tried. The difficulty is that the autonomic nervous system is, by definition, automatic. It responds to how safe or threatened your body feels, which is shaped by past experience, habits and learned associations, not just by what you consciously decide. You can tell yourself there is nothing to worry about and still feel your heart racing.

This is why approaches that work directly with the body’s automatic responses, rather than only with conscious reasoning, can be so helpful. Hypnotherapy is one of them.

The Role of Hypnotherapy in Nervous System Regulation

Hypnosis is a state of focused attention and reduced peripheral awareness, characterised by an enhanced capacity to respond to suggestion (Elkins et al., 2015). It is not sleep, and you remain aware and in control throughout. You can read more about how hypnotherapy works here. There are three main reasons it is particularly suited to calming the nervous system.

1. It shifts the body towards a calmer state

A scoping review of studies measuring the body’s responses during hypnosis found that results “converge to show reductions in sympathetic responses and/or increases in parasympathetic tone under hypnosis” (Fernandez et al., 2022). In practice, that meant changes such as lower heart rate, lower skin conductance (a marker of stress arousal) and heart rate variability patterns associated with parasympathetic activity. In other words, hypnosis tends to ease off the accelerator and apply the brake.

2. It changes how the brain connects with the body

Brain imaging research at Stanford found that during hypnosis, activity decreased in the dorsal anterior cingulate cortex, an area involved in monitoring for threat and conflict. Connectivity increased between the dorsolateral prefrontal cortex and the insula, a region that processes signals from inside the body (Jiang et al., 2017). The authors suggested this may help explain how hypnosis can influence bodily processes such as pain, heart rate and the stress response. Put simply, hypnosis appears to change the conversation between the thinking brain and the body.

3. It helps retrain automatic responses

Relaxation on its own brings short-term relief. What hypnotherapy adds is the chance to rehearse new responses to the specific situations that set off your stress, whether that is a crowded Tube carriage, an email from your manager, a medical appointment or lying in bed at night. Over time, the body can learn to meet those situations with a calmer response. I also teach every client self-hypnosis, so they have a practical way of settling their nervous system between sessions and long after our work together ends.

There is also evidence that this effect reaches beyond how people feel in the moment. In a study of medical students facing exams, those who were trained in hypnosis were, on average, protected from the drop in immune function seen in students who did not receive the training (Kiecolt-Glaser et al., 2001).

Potential Uses of Hypnotherapy for Nervous System Regulation

Because an unsettled nervous system shows up in so many different ways, hypnotherapy can be relevant to a wide range of difficulties. The strength of the evidence varies from area to area, so here is an honest summary.

Anxiety and chronic stress. A 2019 meta-analysis of 15 controlled studies found that hypnosis produced substantial reductions in anxiety compared with control conditions (Valentine et al., 2019). Read more in my guide to hypnotherapy for anxiety and my article on what chronic stress does to your body.

Panic attacks. Panic is the stress response firing at full strength without a real threat. Hypnotherapy helps reduce the body’s sensitivity to the early physical signs that often spiral into panic. See hypnotherapy for panic attacks.

IBS and gut symptoms. This is one of the best-researched uses of hypnotherapy. Gut-directed hypnotherapy is recommended by NICE for people with IBS whose symptoms have not responded to other treatment. In a Swedish study of patients who had received hypnotherapy for IBS, most of those who improved still felt the benefit up to seven years later (Lindfors et al., 2012). Read more in my guide to hypnotherapy for IBS.

Pain. A meta-analysis of 85 controlled experimental trials found that hypnosis produced meaningful pain relief, with the largest benefits in people who respond more readily to hypnosis (Thompson et al., 2019).

Sleep. A systematic review of 24 studies found that just over half reported benefits of hypnosis for sleep, although the authors noted that many of the studies were small and of limited quality (Chamine et al., 2018). In my experience, sleep often improves once the nervous system is calmer during the day. See hypnotherapy for insomnia.

Burnout and overwhelm. Research specific to burnout is still limited, but the same principles apply: reducing ongoing stress arousal, restoring rest, and changing the automatic patterns that keep people pushing past their limits. See hypnotherapy for burnout.

Is Hypnotherapy Right for You?

Hypnotherapy may help if you often feel wired, tense or on edge, if stress is showing up in your body through sleep, digestion or pain, or if you have tried to relax and found your body simply does not follow.

It is not a replacement for medical care. If you have new or unexplained physical symptoms, please see your GP first so that other causes can be ruled out. If you are experiencing severe depression, psychosis or thoughts of harming yourself, please speak to your GP or contact NHS 111 or Samaritans on 116 123. Hypnotherapy works best as part of your overall care, not instead of it.

Frequently Asked Questions

What does “nervous system regulation” actually mean? It means your nervous system can respond to challenges and then return to a calm, balanced state afterwards. A well-regulated system is flexible, not permanently calm.

How quickly can hypnotherapy calm my nervous system? Many people feel noticeably calmer after their first session. Longer-lasting change usually comes from a short course of sessions and regular self-hypnosis practice. I have written more about how many sessions people usually need.

Is hypnotherapy the same as relaxation or meditation? They overlap, as all three can calm the body. Hypnotherapy differs in that it is guided and tailored to you, and it uses suggestion and rehearsal to change specific automatic responses, not only to relax you in the moment.

Can I do this online? Yes. Many of my clients work with me online via Zoom, and the process is the same as in person.

In Person in London or Online

I see clients in person at 364 City Road, London EC1V 2PY, a short walk from Angel and Old Street stations, and online anywhere in the UK and abroad.


Ready to Take the Next Step?

If your body has been stuck in stress mode for too long, you do not have to keep pushing through on your own. I offer a free, no-obligation 15-minute consultation to talk through what you are experiencing and whether hypnotherapy could help.

Book your free consultation or call 020 7101 3284.

References

  1. Chamine, I., Atchley, R. & Oken, B. S. (2018). Hypnosis intervention effects on sleep outcomes: a systematic review. Journal of Clinical Sleep Medicine, 14(2), 271-283. https://doi.org/10.5664/jcsm.6952
  2. Chrousos, G. P. (2009). Stress and disorders of the stress system. Nature Reviews Endocrinology, 5(7), 374-381. https://doi.org/10.1038/nrendo.2009.106
  3. Elkins, G. R., Barabasz, A. F., Council, J. R. & Spiegel, D. (2015). Advancing research and practice: the revised APA Division 30 definition of hypnosis. International Journal of Clinical and Experimental Hypnosis, 63(1), 1-9. https://doi.org/10.1080/00207144.2014.961870
  4. Fernandez, A., Urwicz, L., Vuilleumier, P. & Berna, C. (2022). Impact of hypnosis on psychophysiological measures: a scoping literature review. American Journal of Clinical Hypnosis, 64(1), 36-52. https://doi.org/10.1080/00029157.2021.1873099
  5. Grossman, P. (2023). Fundamental challenges and likely refutations of the five basic premises of the polyvagal theory. Biological Psychology, 180, 108589. https://doi.org/10.1016/j.biopsycho.2023.108589
  6. Jiang, H., White, M. P., Greicius, M. D., Waelde, L. C. & Spiegel, D. (2017). Brain activity and functional connectivity associated with hypnosis. Cerebral Cortex, 27(8), 4083-4093. https://doi.org/10.1093/cercor/bhw220
  7. Kiecolt-Glaser, J. K., Marucha, P. T., Atkinson, C. & Glaser, R. (2001). Hypnosis as a modulator of cellular immune dysregulation during acute stress. Journal of Consulting and Clinical Psychology, 69(4), 674-682. https://doi.org/10.1037/0022-006X.69.4.674
  8. Lindfors, P., Unge, P., Nyhlin, H., Ljótsson, B., Björnsson, E. S., Abrahamsson, H. & Simrén, M. (2012). Long-term effects of hypnotherapy in patients with refractory irritable bowel syndrome. Scandinavian Journal of Gastroenterology, 47(4), 414-420. https://doi.org/10.3109/00365521.2012.658858
  9. McEwen, B. S. (1998). Protective and damaging effects of stress mediators. New England Journal of Medicine, 338(3), 171-179. https://doi.org/10.1056/NEJM199801153380307
  10. National Institute for Health and Care Excellence (2008, updated 2017). Irritable bowel syndrome in adults: diagnosis and management (CG61). https://www.nice.org.uk/guidance/cg61
  11. Porges, S. W. (2007). The polyvagal perspective. Biological Psychology, 74(2), 116-143. https://doi.org/10.1016/j.biopsycho.2006.06.009
  12. Thompson, T., Terhune, D. B., Oram, C., Sharangparni, J., Rouf, R., Solmi, M., Veronese, N. & Stubbs, B. (2019). The effectiveness of hypnosis for pain relief: a systematic review and meta-analysis of 85 controlled experimental trials. Neuroscience & Biobehavioral Reviews, 99, 298-310. https://doi.org/10.1016/j.neubiorev.2019.02.013
  13. Valentine, K. E., Milling, L. S., Clark, L. J. & Moriarty, C. L. (2019). The efficacy of hypnosis as a treatment for anxiety: a meta-analysis. International Journal of Clinical and Experimental Hypnosis, 67(3), 336-363. https://doi.org/10.1080/00207144.2019.1613863
woman online hypnotherapy
Health

What Happens in a Hypnotherapy Session? What to Expect

If you’ve never had hypnotherapy before, it’s natural to feel unsure about what actually happens once you sit down. The good news is there’s nothing mysterious or unsettling about it. A hypnotherapy session is a structured, collaborative conversation designed to help your mind relax and become more open to positive change.

woman online hypnotherapy

What Happens at the Start of a Session?

Your first session usually begins with a conversation, not hypnosis. Antonios will ask about what’s brought you in, your history, and what you’re hoping to achieve. This isn’t small talk, it’s how the therapy gets tailored to you specifically, rather than following a generic script. For issues like anxiety or IBS, this initial discussion also helps identify patterns worth addressing directly in the sessions ahead.

What Does Being “Hypnotised” Actually Feel Like?

Contrary to what films suggest, hypnosis isn’t sleep and you’re not unconscious or out of control. It’s a state of deep relaxation and focused attention, similar to the feeling just before you drift off at night, or the absorption you get watching a film and losing track of time. You remain aware throughout, and you can hear everything being said. Most people describe it as calming rather than strange.

What Does the Hypnotherapist Actually Do?

Once you’re relaxed, Antonios uses an Ericksonian approach, which is gentle, permissive, and conversational rather than direct commands. This might involve guided imagery, metaphor, or suggestions tailored to your specific goals, whether that’s reducing anxiety, calming an overactive gut, or building confidence. The language used is designed to work with your mind’s own resources, not against them, which is part of why the approach tends to feel comfortable rather than forceful.

How Long Does a Session Last, and How Many Will I Need?

A typical session runs around 60 minutes. The number of sessions varies depending on the issue, but many people notice meaningful shifts within 4 to 6 sessions. Some goals, like specific phobias, can respond in fewer sessions, while more established patterns, such as long-standing anxiety or IBS, often benefit from a slightly longer course of structured work.

What Happens After the Session Ends?

You’ll come out of the relaxed state feeling calm and alert, not groggy or disoriented. Many clients describe feeling lighter or clearer afterward. Antonios will usually check in on what you noticed, and may suggest simple things to reflect on or practise before your next session, so the changes continue to settle between appointments.

Is It Different Online Compared to In Person?

Not in any way that affects the results. Sessions run over Zoom follow exactly the same structure as in-person appointments, and research shows online hypnotherapy can be just as effective. This means you can access the same quality of support wherever you’re based, without needing to travel to central London.

Key Takeaways

  • A hypnotherapy session starts with conversation, not hypnosis, so the work is tailored to you
  • Hypnosis is a state of relaxed, focused attention, not sleep or loss of control
  • Antonios uses an Ericksonian, permissive style rather than direct commands
  • Sessions typically last around 60 minutes, with many people noticing change within 4 to 6 sessions
  • Online sessions follow the same structure and effectiveness as in-person appointments

If you’ve been curious about hypnotherapy but weren’t sure what to expect, hopefully this has taken away some of the mystery. Antonios offers sessions both in person in Angel, London and online, so you can start wherever feels most comfortable. Book a free consultation to ask any questions and see if it’s the right fit for you.

References

Woman having online hypnotherapy
Health

Hypnotherapist Near Me in London: A Practitioner’s Guide to Choosing the Right One

If you have typed “hypnotherapist near me” into Google this week, you are probably not idly browsing. You are likely dealing with something that has become too heavy to carry alone, whether that is anxiety that flares on the Tube, a sleep problem that has gone on for months, or a habit you have tried to break a dozen times without success. The search itself is often the first act of taking that problem seriously.

I am Antonios Koletsas, a clinical hypnotherapist practising from City Road, close to Angel and Old Street. I want to use this article slightly differently to how most local guides are written. Rather than simply telling you why my practice is nearby and convenient, I want to walk you through what actually matters when you are choosing a hypnotherapist in London, so that whoever you end up sitting across from, you are making an informed decision rather than a hopeful guess.

Emotional Eating Hypnotherapy

Why “Near Me” Still Matters, Even With Online Options

Online hypnotherapy has genuinely changed what is possible. I see clients across the UK and beyond through online hypnotherapy sessions, and the clinical results are comparable to in-person work for most presentations. So why does location still show up in almost every search for a hypnotherapist?

In my experience, three things are usually behind it. First, some people simply feel more contained and supported in a physical room, particularly for the first session, before trust has been built. Second, proximity makes consistency easier. A hypnotherapist five minutes from your office or your home is one you will actually get to on a difficult week. Third, and perhaps most understated, choosing someone local often reflects a wish to work with a real person embedded in your city rather than a name on a directory. A City Road practice serving Islington, Clerkenwell, Shoreditch, Finsbury and the wider City is not just a pin on a map. It is a practitioner who understands the pace of London life, the commuter anxiety of the Underground, and the particular kind of burnout that comes from working in this city.

What to Check Before You Book Anyone

The word “hypnotherapist” is not a protected title in the UK, which means anyone can use it regardless of training. This is the single most important thing to understand before you book, and it is the filter I would encourage you to apply to any practitioner, including me.

Registration and accreditation

Look for registration with a recognised accrediting body such as the General Hypnotherapy Standards Council (GHSC) or the General Hypnotherapy Register (GHR). These organisations set training standards, hold practitioners to a code of ethics, and provide a route for complaints if something goes wrong. I am registered with both, alongside the National Hypnotherapy Society, and you can verify this independently rather than taking my word for it.

The training pathway behind the qualification

Ask where the practitioner trained and under whom. Diploma quality varies enormously across the UK hypnotherapy training landscape. I trained under Stephen Brooks at BHRTI in the Ericksonian approach, which is a specific, research-referenced methodology rather than a generic script-based technique. Knowing the training lineage tells you far more than a certificate alone.

Specialism relevant to your actual problem

A hypnotherapist who treats everything from smoking cessation to sports performance to trauma may be a generalist, which suits some presentations well. For others, particularly clinical conditions like IBS or panic disorder, a practitioner with specific, evidenced experience in that area tends to get better outcomes. I focus on anxiety and panic attacks, social anxiety, phobias, insomnia, burnout, and gut-directed hypnotherapy for IBS, the last of which is one of the few hypnotherapy approaches backed by NICE guidance and a substantial evidence base from the Whorwell protocol.

Hypnotherapy Near Angel, Islington and Central London

My practice sits at 364 City Road, London EC1V 2PY, a short walk from both Angel and Old Street stations. This puts the clinic within easy reach if you are coming from Islington, Clerkenwell, Shoreditch, Finsbury, King’s Cross, Hackney, or the wider City. Many of my clients are working professionals who fit a session in before or after work, which is one of the practical advantages of a central London location over a practice tucked away in the outer boroughs.

That said, I would rather you choose well than choose close. If a practitioner elsewhere in London or online is the better clinical fit for what you are dealing with, that matters more than a shorter commute. This is exactly why the checklist above comes before the map pin.

In-Person or Online: Which Actually Suits You

I get asked this often enough that it is worth addressing directly. In-person sessions at the City Road practice tend to suit people who want a clear boundary between the therapy space and home, or who are new to hypnotherapy and want the reassurance of a dedicated room. Online sessions suit people with unpredictable schedules, those outside London, or clients who have already worked with me and are continuing maintenance sessions. Clinically, I do not see a meaningful difference in outcomes between the two formats once someone is comfortable with the medium. You can read more about how online hypnotherapy works in practice if that route suits your circumstances better.

What Actually Happens in a First Session

A good first session should never involve being hypnotised on the spot with no context. When you book with me, we begin with a consultation to understand what has brought you in, what you have already tried, and what you want to change. I explain the Ericksonian approach I use, because understanding the process reduces the apprehension most first-time clients arrive with. Only once that groundwork is in place do we move into the hypnotic work itself, which is a collaborative, fully conscious process rather than something done to you.

Frequently Asked Questions

How do I find a genuinely good hypnotherapist near me in London? Start with registration status (GHSC or GHR), then check their specific training lineage and whether their stated specialisms match your presentation. Location is a legitimate factor for convenience, but it should be the last filter you apply, not the first.

Is hypnotherapy regulated in the UK? Not by statute. “Hypnotherapist” is not a protected title, so voluntary registers like the GHSC and GHR are currently the closest thing to a quality standard, and checking a practitioner’s registration is the most reliable way to protect yourself.

How much does hypnotherapy cost in London? Fees vary by practitioner and format. You can see my current session fees for both in-person and online work on the fees page.

How many sessions will I need? This depends entirely on what you are working on. Some clients notice change within three to four sessions, particularly for specific phobias, while conditions like IBS or long-standing anxiety often benefit from a slightly longer course. I discuss a realistic estimate during your initial consultation rather than committing you to a fixed package upfront.

Do I need a GP referral to see a hypnotherapist? No, hypnotherapy is accessed privately in the UK and you can book directly. That said, I do receive clinical referrals from gastroenterology teams, including OneWelbeck and The London Clinic, for gut-directed work, and I am happy to liaise with your GP or consultant if that is useful to your care.

Ready to Take the Next Step

If you have read this far, you have already done more due diligence than most people manage before booking a hypnotherapist, and that matters. Whether you decide to work with me at City Road, near Angel and Old Street, or choose another registered practitioner elsewhere in London, I would rather you make that decision well informed than in a hurry.

If what I have described here sounds like the right fit, you can book a free consultation or call me directly on 020 7101 3284 to talk through what you are dealing with before committing to anything.

References

  • General Hypnotherapy Standards Council (GHSC). Practitioner Registration Standards.
  • General Hypnotherapy Register (GHR). Code of Ethics and Practice.
  • National Institute for Health and Care Excellence (NICE). NG155, CG113, CG159.
  • Whorwell, P.J. et al. Gut-directed hypnotherapy for irritable bowel syndrome.
  • Kirsch, I., Montgomery, G. & Sapirstein, G. (1995). Hypnosis as an adjunct to cognitive-behavioral psychotherapy: A meta-analysis. Journal of Consulting and Clinical Psychology.

About the Author

Antonios Koletsas is a clinical hypnotherapist based at 364 City Road, London EC1V 2PY, near Angel and Old Street. Trained in Ericksonian Hypnotherapy under Stephen Brooks at BHRTI and holding the HypnoIBS Diploma, he is registered with the GHSC and GHR and receives gastroenterology referrals from OneWelbeck and The London Clinic. He works with clients across London and online throughout the UK on anxiety, panic disorder, phobias, insomnia, IBS, and burnout.

tinnutus Hypnotherapy
Uncategorized

Why Tinnitus Feels Louder at Night (and How Hypnotherapy Breaks the Cycle)

Almost every client who comes to see me about tinnitus tells me some version of the same thing. During the day, the noise is manageable. They can work, talk, get on with things. But the moment the lights go off and the house goes quiet, the ringing seems to grow. It fills the room. It fills their head. And with it comes a familiar spiral of frustration, worry, and the dread of another sleepless night.

If this sounds like you, I want to start by saying something that often brings genuine relief in itself: your tinnitus has not actually got louder at night. What has changed is your brain’s relationship with it. Understanding that difference is the first step toward loosening its grip, and it is also the foundation of how I work with tinnitus using Ericksonian hypnotherapy here in London.

tinnutus Hypnotherapy

Tinnitus Is a Perception, Not Just a Sound

Tinnitus is the experience of hearing sound, often a ringing, buzzing, hissing, or humming, when there is no external source producing it. According to the NHS and the British Tinnitus Association, it affects a significant proportion of UK adults at some point in their lives, and for many it becomes a long-term, fluctuating companion rather than a one-off event.

What matters clinically is that tinnitus is generated, at least in part, within the auditory and limbic pathways of the brain rather than the ear itself. The National Institute for Health and Care Excellence, in its guideline on tinnitus assessment and management (NICE NG155), sets out a stepped approach that treats tinnitus not as a single fixed symptom but as something whose impact depends heavily on attention, emotional state, and coping response. This is precisely why two people can have an audiologically identical level of tinnitus and experience wildly different levels of distress from it.

The Nighttime Amplification Effect

There is nothing mysterious about why tinnitus seems to swell after dark. Several ordinary mechanisms combine at once.

Reduced environmental masking. During the day, traffic, conversation, and general background noise partially cover the internal sound. At night, that masking layer disappears, so the same physical signal becomes proportionally louder against a silent backdrop.

A quieter mind has fewer places to look. In daylight hours, attention is pulled outward toward tasks, people, and screens. In bed, with nothing left to do, attention naturally turns inward, and the auditory system becomes the most available thing to notice. What you attend to, your brain amplifies. This is a basic feature of how the nervous system prioritises information, not a flaw in your character or willpower.

The anticipatory anxiety loop. This is the piece I see doing the most damage, and it is the same mechanism I address when working with clients on panic attacks and health anxiety. Many people with tinnitus begin anticipating the noise before they have even got into bed. The thought “here we go again” triggers a small stress response, which raises physiological arousal, which in turn makes the auditory and limbic systems more reactive, which makes the tinnitus more noticeable, which confirms the fear, which deepens the anticipation the next night. Within a few weeks, the bed itself becomes a conditioned cue for vigilance rather than rest.

Cortisol and the stress-tinnitus feedback loop. Elevated stress hormones sensitise the central auditory pathways, and disrupted sleep in turn raises cortisol the following day. This is a genuine physiological loop, not simply “being anxious about a sound,” and it explains why standard advice to just relax rarely works on its own. The loop needs to be interrupted at the level where it is actually maintained: the nervous system’s threat appraisal, not the ear.

Why This Matters More Than the Sound Itself

I want to be clear with every client, and I will be equally clear here: hypnotherapy does not claim to eliminate the physical origin of tinnitus, and if you have not already done so, you should have your tinnitus assessed by a GP or audiologist first, in line with NICE guidance, to rule out treatable causes such as earwax, infection, or medication side effects.

What hypnotherapy addresses is the second half of the equation, the part that determines whether tinnitus becomes a minor background hum you barely register or a nightly source of dread. Audiological research on tinnitus habituation, published in journals indexed on PubMed, consistently shows that reducing the emotional salience of the sound, rather than the sound itself, is what predicts long-term improvement in quality of life. This is exactly the territory in which clinical hypnotherapy operates.

How Ericksonian Hypnotherapy Retrains the Response

My Ericksonian hypnotherapy approach, trained originally at BHRTI under Stephen Brooks and refined through the HypnoIBS Diploma and years of clinical practice, does not rely on scripted suggestion alone. It works with the client’s own internal resources, using the same principle that underpins Milton Erickson’s original work: the subconscious mind already knows how to filter out repetitive, unthreatening stimuli, because it does this automatically with hundreds of sensations every day, from the feeling of your clothes against your skin to the hum of a refrigerator. Tinnitus has simply been flagged, mistakenly, as important and threatening.

In sessions, I typically work across three interconnected layers.

Downregulating the threat response. Through deep trance states and guided relaxation, we lower the baseline physiological arousal that keeps the auditory system on high alert. This directly targets the cortisol-tinnitus loop described above.

Reframing the meaning of the sound. Using Ericksonian language patterns and metaphor, we gently shift the subconscious classification of the tinnitus from “danger signal requiring vigilance” to “neutral background noise,” in the same way your brain already ignores the sound of your own breathing.

Rebuilding the association with rest. For clients whose tinnitus is worst at bedtime, we work specifically on decoupling the bed from anticipatory anxiety, restoring it as a cue for sleep rather than dread. This overlaps closely with the work I do with clients experiencing insomnia, since the two conditions frequently arrive together.

Most clients notice a meaningful shift in perceived loudness and distress within three to five sessions, though chronic or long-standing cases sometimes benefit from occasional follow-up sessions to reinforce the new pattern.

What a Session Looks Like

I see clients for tinnitus both in person at my practice near Angel and Old Street, and via online hypnotherapy for those who prefer to work from home or who are based outside London. Each programme begins with a full clinical history, since tinnitus can have multiple contributing factors, including stress, TMJ tension, and unresolved trauma, all of which I assess before building an individual treatment plan rather than applying a generic script.

Frequently Asked Questions

Can hypnotherapy cure tinnitus completely? Hypnotherapy does not remove the underlying physiological source of tinnitus. What it reliably achieves is a significant reduction in how loud and intrusive the sound feels, by changing the brain’s attention and stress response to it. For many clients, this is functionally indistinguishable from resolution in daily life.

Why does my tinnitus wake me up specifically at 2 or 3am? This often coincides with a natural dip in the body’s cortisol rhythm followed by a rebound, combined with the total absence of masking noise during the deepest, quietest part of the night. It is a physiological pattern, not a sign that your condition is worsening.

Is tinnitus linked to anxiety, or does anxiety cause tinnitus? The relationship runs in both directions. Anxiety heightens the nervous system’s sensitivity to internal sounds, and living with unpredictable tinnitus understandably generates anxiety. This is why treating the anxiety component, rather than only the auditory symptom, tends to produce the most durable relief.

How many sessions of hypnotherapy will I need for tinnitus? Most clients report noticeable change within three to five sessions, with some choosing occasional maintenance sessions afterwards, particularly during stressful periods when tinnitus tends to flare.

Should I see a doctor before starting hypnotherapy for tinnitus? Yes. Always have new or worsening tinnitus assessed by a GP or ENT specialist first, particularly if it is sudden, one-sided, or accompanied by hearing loss or dizziness, in order to rule out any condition requiring medical treatment. Hypnotherapy works alongside medical care, not instead of it.

Clinical References


If tinnitus has been keeping you up at night, you do not have to simply live with it. I offer tinnitus hypnotherapy in London and online, working with the anxiety and attentional patterns that keep the noise front and centre. Book your free consultation today, or call me directly on 020 7101 3284 to discuss whether hypnotherapy is right for you.

Quit Smoking
Health

Stop Smoking Hypnotherapy in London: Can It Really Help You Quit?

If you’ve tried patches, gum, willpower, or simply hoping this pack will be your last, you’re not alone. Stop smoking hypnotherapy in London has become a popular option for people who feel the habit runs deeper than nicotine alone. Most smokers already know the health risks. Knowing has never been the problem. The problem is that smoking has woven itself into your routines, your stress responses, and your identity in ways that logic alone can’t untangle. Here’s an honest look at how hypnotherapy approaches that, what the research says, and whether it might suit you.

stop smoking hypnotherapy

Why Is Quitting Smoking So Hard, Even When You Want To?

Nicotine is addictive, yes. But if nicotine were the whole story, patches and gum would work for almost everyone, and they don’t. What makes smoking so stubborn is that it operates on two levels at once. There’s the chemical dependency, which fades within days to weeks. And then there’s the behavioural and emotional layer: the cigarette with your morning coffee, the one after a difficult meeting, the excuse to step outside and breathe for five minutes, the way it punctuates your day.

That second layer is where most quit attempts fall apart. You can white-knuckle through cravings for a fortnight, then one stressful afternoon the old pattern reasserts itself before you’ve consciously decided anything. That’s not weakness. It’s simply how habits work. They live in the automatic, unconscious part of the mind, which is exactly the part that willpower struggles to reach and exactly the part hypnotherapy is designed to work with.

How Does Hypnotherapy for Smoking Work?

Hypnotherapy for smoking works by addressing the habit at the level where it actually lives, your unconscious patterns. In a session, you’re guided into a relaxed, focused state, a bit like the absorbed feeling of being lost in a good book or driving a familiar route on autopilot. You’re not asleep and you’re not under anyone’s control. You’re simply in a state where the mind is more open to updating old associations.

From there, the work is about loosening the links that keep smoking automatic. The coffee-and-cigarette pairing. The stress-then-smoke reflex. The belief that a cigarette actually relaxes you, when in reality it mostly relieves the withdrawal the last cigarette created. We also build up what you’re moving towards: easier breathing, food tasting better, money staying in your pocket, the quiet pride of being someone who doesn’t smoke.

At London Hypnotics, I work in the Ericksonian tradition, which means no swinging watches and no commands barked at you. It’s a collaborative, permissive process. Rather than telling your mind what to do, Ericksonian hypnotherapy invites it to find its own route to the change you’ve already decided you want. Many clients find this approach feels respectful and surprisingly natural, especially if they’ve been put off by the stage-hypnosis stereotype.

Does Hypnotherapy Actually Help You Quit Smoking?

The evidence is promising, but honest practitioners will tell you it’s mixed. Some randomised trials have found hypnotherapy outperforming nicotine replacement therapy alone, with participants more likely to be smoke-free at follow-up. Larger systematic reviews, including Cochrane’s, conclude that while results are encouraging, the studies vary in quality and more rigorous research is needed before firm claims can be made.

What does seem consistent across the research and clinical experience is this: hypnotherapy helps most when two conditions are met. First, you genuinely want to stop. Hypnotherapy amplifies motivation that’s already there. It can’t install a desire to quit that doesn’t exist, and anyone who promises otherwise is overclaiming. Second, the work addresses what smoking has been doing for you, not just the smoking itself. For many people, cigarettes are a coping mechanism for stress or anxiety. If we remove the cigarette but leave the stress untouched, the mind will go looking for a replacement. Quitting sticks when you have something better to cope with, which is why sessions often include practical tools for calming your nervous system without reaching for a lighter.

How Many Sessions Do You Need to Stop Smoking?

Many hypnotherapists offer smoking cessation in one to three sessions, and that’s broadly my approach too. A typical structure looks like this: an initial consultation to understand your smoking history, your triggers, and your reasons for quitting, followed by one longer session targeting the habit itself. A follow-up session a week or two later reinforces the change, handles any wobbles, and adjusts the approach if certain triggers are proving stickier than expected.

Some people genuinely do stop after a single session. Others benefit from the follow-up work, particularly heavy smokers or anyone whose smoking is tightly bound to stress, poor sleep, or social situations involving alcohol. If underlying issues like insomnia or chronic stress are fuelling the habit, we may spend some time there too, because a calmer, better-rested nervous system makes quitting considerably easier. There’s no prize for doing it in the fewest sessions possible. The prize is staying stopped.

What Happens in a Stop Smoking Hypnotherapy Session?

If you’ve never had hypnotherapy before, it’s natural to feel a little unsure about what you’re walking into. A first session usually begins with conversation, not trance. We talk about when you smoke, what tends to trigger it, what you’ve tried before, and crucially, why you want to stop now. Your own reasons, in your own words, become the raw material for the hypnotic work.

The hypnosis itself is comfortable and unremarkable in the best way. You sit back, close your eyes if you like, and follow my voice. Most people describe it as deeply relaxing. You remain aware throughout, you can speak if you need to, and you couldn’t be made to do anything against your values. Afterwards, most clients leave feeling calm and clear-headed, often with a slightly surprised sense that the cigarette they’d normally want simply doesn’t appeal.

Is Online Hypnotherapy Effective for Quitting Smoking?

Yes. Hypnotherapy relies on focused attention and imagination, both of which work perfectly well over a video call. Many clients actually find it easier to relax in their own home, in their own chair, without travel on either side of the session. All you need is a quiet room, a stable connection, and headphones if you have them.

So whether you’re around the corner from my practice in Angel or elsewhere in the UK, online sessions are a genuine option, not a compromise. The structure, the techniques, and the results are the same.

Hypnotherapy vs Patches, Gum, and Willpower: How Does It Compare?

These approaches aren’t rivals, and they target different parts of the problem. Nicotine replacement therapy manages the chemical withdrawal. Willpower manages moment-to-moment decisions, at least until it runs out. Hypnotherapy works on the habit architecture underneath: the triggers, associations, and self-image that keep pulling you back to smoking long after the nicotine has left your system.

For some people, combining approaches makes sense. There’s no conflict in using hypnotherapy alongside NHS stop smoking support or nicotine replacement if your GP recommends it. What hypnotherapy adds is the piece the others tend to miss: changing how you relate to cigarettes, so that not smoking stops feeling like deprivation and starts feeling like relief.

Key Takeaways

  • Stop smoking hypnotherapy targets the unconscious habits, triggers, and associations behind smoking, not just the nicotine.
  • Quitting is hard because smoking operates on two levels: chemical dependency, which fades quickly, and behavioural habit, which is where most relapses happen.
  • Evidence is promising, particularly when hypnotherapy also addresses the underlying stress and anxiety that keep the habit in place.
  • Most smoking cessation programmes take one to three sessions, with a follow-up to reinforce the change.
  • Online hypnotherapy is just as valid as in-person work for quitting smoking, and it combines comfortably with NHS support or nicotine replacement if needed.
  • Motivation matters: hypnotherapy amplifies your desire to quit, it doesn’t replace it.

If you’re ready to stop smoking for good, I’d love to help. I’m Antonios, a GHSC and CNHC registered clinical hypnotherapist, and I offer sessions both in person in Angel, London and online across the UK. You can book a free consultation to talk through your smoking history, ask any questions, and see whether hypnotherapy feels like the right fit for you. No pressure, just a conversation.

References

Woman having online hypnotherapy
Health

How Many Hypnotherapy Sessions Do You Need to See Results?

If you’re considering hypnotherapy, one of the first questions you’ll probably ask is how many sessions you’ll actually need. The honest answer is that it depends on what you’re working on, but most people notice change within four to eight sessions, and some issues can be addressed in even fewer.

How many sessions does hypnotherapy usually take?

For a single, well-defined issue such as a fear of flying or public speaking, three to six sessions is typical. For more embedded patterns like generalised anxiety or long-standing insomnia, six to twelve sessions tends to give a more lasting result. Gut-directed hypnotherapy for IBS generally follows a structured protocol of around six to eight sessions, since it’s retraining the gut-brain connection rather than addressing a single trigger.

What affects how many sessions I’ll need?

A few things shape the number. How long you’ve had the issue matters; a pattern that’s been in place for twenty years usually takes longer to shift than something that started three months ago. How responsive you are to hypnotic suggestion plays a part too, though this varies far less between people than most assume. And whether you’re dealing with one clear issue or several overlapping ones (say, anxiety that’s also disrupting your sleep) will naturally extend the work.

hypnotherapy for IBS session

Will I feel a difference after just one session?

Often, yes, at least in terms of how calm and clear-headed you feel afterwards. But one session rarely creates lasting change on its own. Think of it like exercise: one good session with a personal trainer might leave you feeling great, but the fitness gains come from consistency. Hypnotherapy works the same way, each session builds on the last, reinforcing new patterns until they hold on their own.

Is there a point where more sessions stop helping?

Generally, yes. Most protocols are designed with a natural endpoint, once the new pattern is established, ongoing sessions have diminishing returns. At London Hypnotics, Antonios reviews progress regularly and will tell you honestly if he thinks you’ve reached a good stopping point, rather than keeping sessions going indefinitely.

What if I don’t see results in the expected number of sessions?

This happens sometimes, and it’s worth talking about openly rather than assuming hypnotherapy “doesn’t work for you.” Occasionally the initial goal needs adjusting, or there’s an underlying factor that wasn’t clear at the start. A good hypnotherapist will revisit the approach with you rather than simply extending the session count.

Key Takeaways

  • Most single-issue concerns respond within three to six sessions.
  • Gut-directed hypnotherapy for IBS typically follows a six to eight session protocol.
  • How long you’ve had the issue and how many concerns you’re addressing both affect the timeline.
  • Change is usually cumulative, one session can feel good, but lasting results build over several.
  • Progress should be reviewed regularly, not assumed to need an open-ended number of sessions.

If you’re unsure how many sessions your particular situation might need, the easiest next step is to talk it through directly. Antonios offers sessions in person in Angel, London and online, and you’re welcome to book a free consultation to discuss what a realistic plan would look like for you.

References

  • [1] National Institute for Health and Care Excellence (NICE), 2017. Irritable bowel syndrome in adults: diagnosis and management (CG61). https://www.nice.org.uk/guidance/cg61
  • [2] Palsson, O.S., 2015. Standardized Hypnosis Treatment for Irritable Bowel Syndrome: The North Carolina Protocol. American Journal of Clinical Hypnosis.
  • [3] British Psychological Society, Division of Health Psychology. General guidance on psychological therapy dosage and treatment length.
Milton Erickson
Health

What Is Ericksonian Hypnotherapy and How Does It Work?

If you have ever pictured hypnotherapy as someone swinging a pocket watch and barking commands, Ericksonian hypnotherapy is something quite different. Developed by the American psychiatrist Milton H. Erickson, this approach uses subtle, conversational language to help your mind shift perspective and access its own capacity for change. At London Hypnotics, Ericksonian principles sit at the heart of every session.

Who was Milton Erickson, and why does it matter?

Milton H. Erickson (1901–1980) was a psychiatrist and psychologist widely regarded as the most influential hypnotherapist of the twentieth century. Unlike his contemporaries, Erickson rejected the idea that a therapist must issue direct commands to produce change. Instead, he observed that people enter natural trance states every day, and that carefully chosen language, stories, and metaphors could work with those states rather than against them. His methods became the foundation for approaches including Neuro-Linguistic Programming (NLP) and solution-focused therapy.

Milton Erickson

How does Ericksonian hypnotherapy differ from traditional hypnosis?

Traditional, or “authoritarian,” hypnotherapy relies on direct suggestion: “You will feel calm. You will not crave cigarettes.” Ericksonian hypnotherapy is permissive by design. Rather than telling the mind what to do, it uses indirect language, therapeutic metaphor, and collaborative conversation to invite the unconscious to find its own solutions. This matters because resistance is far less likely when nothing is being imposed. For people who feel sceptical about hypnosis, or who have tried direct-suggestion approaches without success, the Ericksonian model is often a better fit.

What happens during an Ericksonian hypnotherapy session?

Sessions begin with an open conversation about what you want to change and what has kept that change just out of reach. From there, a light to medium trance state is invited through relaxed, rhythmic language rather than a formal induction script. Within that state, carefully crafted stories, questions, and imagery help the unconscious mind rehearse new responses. Sessions feel more like a deep, absorbed conversation than the dramatic “sleep now” scenes shown in films. Most people describe feeling pleasantly relaxed and surprisingly clear-headed afterwards.

What conditions can Ericksonian hypnotherapy help with?

The approach is flexible enough to apply across a wide range of concerns. Clinical evidence supports gut-directed hypnotherapy for IBS, where indirect suggestion helps calm the gut-brain communication loop that drives symptoms. Ericksonian techniques are also well-suited to anxiety, performance concerns, low confidence, chronic stress, and sleep difficulties. Because the method works with the individual’s own language and mental imagery rather than a fixed script, it adapts well to complex or longstanding problems.

Is Ericksonian hypnotherapy evidence-based?

Hypnotherapy as a clinical intervention has a growing evidence base, particularly for IBS and anxiety. Erickson’s specific techniques are harder to isolate in randomised controlled trials because they are inherently tailored to each individual, but the underlying mechanisms, including focused attention, expectancy, and therapeutic suggestion, are well documented in cognitive neuroscience. Practitioners registered with the GHSC and CNHC, as Antonios is, are bound by professional standards that require practice grounded in current evidence.

Key Takeaways

  • Ericksonian hypnotherapy was developed by psychiatrist Milton H. Erickson and uses indirect, conversational language rather than direct commands.
  • It works with the unconscious mind through metaphor, storytelling, and permissive suggestion, making it accessible to people who are sceptical or resistant to traditional hypnosis.
  • Sessions feel collaborative and conversational, not theatrical or prescriptive.
  • It has clinical applications across IBS, anxiety, sleep problems, stress, and confidence, and forms the methodological foundation at London Hypnotics.
  • Practitioners registered with professional bodies such as the GHSC and CNHC are held to evidence-informed standards of practice.

If you are curious whether Ericksonian hypnotherapy could help with something you are dealing with, Antonios offers a free initial consultation with no obligation. You are welcome to book a free consultation and ask any questions before committing to anything.

References

  • [1] Erickson, M.H., Rossi, E.L. & Rossi, S.I. (1976). Hypnotic Realities: The Induction of Clinical Hypnosis and Forms of Indirect Suggestion. Irvington Publishers.
  • [2] Elkins, G., Barabasz, A., Council, J. & Spiegel, D. (2015). Advancing Research and Practice: The Revised APA Division 30 Definition of Hypnosis. International Journal of Clinical and Experimental Hypnosis, 63(1), 1–9. https://pubmed.ncbi.nlm.nih.gov/25365127/
  • [3] Whorwell, P.J., Prior, A. & Faragher, E.B. (1984). Controlled trial of hypnotherapy in the treatment of severe refractory irritable-bowel syndrome. The Lancet, 324(8414), 1232–1234. https://pubmed.ncbi.nlm.nih.gov/6150275/
IBS FOOD TO AVOID
Health

IBS-D Hypnotherapy in London: Gut-Directed Treatment for Diarrhoea-Predominant IBS

For a condition that affects roughly one in ten adults in the UK, diarrhoea-predominant IBS is remarkably under-discussed. People will talk at length about stress, about sleep, even about constipation with relative ease. Urgency and unpredictable bowel movements tend to stay private. Clients often arrive at my practice having managed IBS-D quietly for years, sometimes a decade or more, before deciding that mapping every outing around toilet access is no longer a sustainable way to live.

This article looks at what is actually happening in the body during diarrhoea-predominant IBS, why the condition is so resistant to dietary change alone, and how gut-directed hypnotherapy addresses the nervous system mechanisms that are usually driving it.

IBS FOOD TO AVOID

What IBS-D Actually Is

IBS-D is one of four recognised IBS subtypes under the Rome IV diagnostic criteria, alongside IBS-C (constipation-predominant), IBS-M (mixed), and IBS-U (unclassified). It is characterised by recurrent abdominal pain associated with loose or watery stools occurring on at least a quarter of symptomatic days, frequently accompanied by urgency, a sense of incomplete evacuation, bloating, and cramping that tends to ease after a bowel movement.

What distinguishes IBS-D clinically from other gastrointestinal conditions is the absence of structural disease. Investigations such as colonoscopy, blood tests, and stool studies typically return normal results. This is not a reassurance that always lands well with clients, many of whom would, in some sense, prefer a clear structural explanation. Instead, what is usually present is a disorder of gut-brain communication, in which the enteric nervous system and the central nervous system have become miscalibrated in their regulation of motility, secretion, and pain perception.

It is worth noting that conditions with overlapping presentations, including inflammatory bowel disease, coeliac disease, microscopic colitis, and bile acid malabsorption, should be ruled out by a GP or gastroenterologist before a diagnosis of IBS-D is settled on. This article concerns the functional presentation once those have been appropriately excluded.

Why the Gut Moves Too Fast

In IBS-C, the dominant mechanism is suppressed motility under chronic sympathetic arousal. IBS-D tends to involve the opposite pattern: accelerated colonic transit, heightened secretory activity, and a lowered threshold for the gastrocolic reflex, the contraction that prompts the urge to defecate after eating or under stress.

The enteric nervous system, sometimes called the body’s second brain, contains around 500 million neurons and communicates continuously with the central nervous system via the vagus nerve and the hypothalamic-pituitary-adrenal axis. In IBS-D, this communication appears to run in a particular direction: psychological stress and anticipatory anxiety trigger the release of corticotropin-releasing hormone, which in turn accelerates gut motility and increases intestinal permeability. The result is a digestive system primed to react quickly, often at precisely the moments when speed is least convenient.

This is compounded by visceral hypersensitivity, a well-documented feature of IBS in which normal levels of gut distension are perceived as painful or urgent. The gut is not necessarily producing more waste or moving more dramatically than a healthy gut. It is signalling more loudly, and the brain is interpreting those signals through a lens of alarm.

The Anticipation Problem

The defining feature I see clinically in IBS-D, more than the diarrhoea itself, is the anticipatory anxiety that builds around it. Once someone has experienced urgency in an inconvenient setting, a meeting, a train, a first date, the subconscious files that event as evidence of a specific danger. It then begins scanning for early signs: a flicker of cramping, a change in the texture of breakfast, the length of a commute without toilet access.

This hypervigilance is entirely understandable, and it is also the mechanism that perpetuates the cycle. Monitoring the gut for signs of trouble raises sympathetic arousal, and sympathetic arousal is precisely what accelerates gut motility in IBS-D. The vigilance generates the very urgency it is trying to prevent. Many clients describe restructuring their entire lives around this fear: declining invitations, mapping toilets before any journey, avoiding certain foods not because of a confirmed intolerance but because of what happened the last time. Life contracts around the unpredictability, often more severely than the physical symptoms alone would justify.

This pattern has clear parallels with what I see in clients presenting with panic attacks: a single distressing episode generates a fear-of-fear cycle that becomes more limiting than the original event. In both cases, the nervous system has learned a threat association that now needs to be unlearned, and that unlearning happens more effectively at the subconscious level than through conscious reassurance alone.

Where Dietary Approaches Reach Their Limit

The low-FODMAP diet, developed at Monash University, has a meaningful evidence base for IBS and is often the first intervention a GP or dietitian recommends. For many people with IBS-D, it reduces the fermentable substrates contributing to bloating and loose stools, and I would never discourage a client from pursuing it under proper dietetic guidance.

What diet cannot do is recalibrate a nervous system that has learned to treat ordinary gut sensations as emergencies. Clients frequently describe partial improvement on a restricted diet followed by a plateau, or symptoms that persist on “safe” days for no identifiable dietary reason. This is consistent with what the research shows: dietary intervention addresses the gut’s chemical environment, while gut-directed hypnotherapy addresses the regulatory signalling between brain and gut. The two are not competing approaches. For many clients, they work most effectively in combination.

How Gut-Directed Hypnotherapy Addresses IBS-D

Gut-directed hypnotherapy was developed by Professor Peter Whorwell at the University of Manchester and is referenced in NICE guidance for IBS. While much of the original protocol research focused on mixed IBS populations, subsequent trials, including work by Lacy and colleagues and the Monash comparative trial against low-FODMAP, have demonstrated robust symptom improvement across IBS subtypes, including IBS-D specifically.

Calming the Sympathetic Drive

The hypnotic state is a measurable activator of the parasympathetic nervous system. Research has documented reductions in heart rate, cortisol, and sympathetic tone during hypnosis. For IBS-D, where sympathetic activation directly accelerates motility and secretion, this downregulation is not incidental relaxation. It addresses the physiological driver of the symptom itself. Clients often notice a reduction in the frequency and intensity of urgent episodes before any gut-specific suggestion work has even been introduced, simply as a function of a generally calmer baseline nervous system.

Direct Suggestion and Gut-Focused Imagery

Within the hypnotic state, suggestion and imagery are used to influence the smooth muscle activity of the colon and the sensitivity of the gut’s nerve endings. For IBS-D specifically, this often involves imagery oriented around steadiness, predictability, and a slowing of transit, alongside suggestion designed to recalibrate the gastrocolic reflex so that ordinary triggers, eating, mild stress, travel, no longer prompt an exaggerated response.

Reducing Visceral Hypersensitivity

A core mechanism in gut-directed hypnotherapy is the reduction of visceral hypersensitivity, supported by neuroimaging research showing that hypnosis measurably changes how the brain processes signals from the gut. For IBS-D, this translates into a gradual reinterpretation of gut sensations from threatening to neutral, reducing the urgency response to normal levels of bowel activity.

Working With the Anticipatory Anxiety

Using Ericksonian techniques, indirect and tailored to the individual rather than delivered as a fixed script, we work specifically on the hypervigilance and anticipatory dread that have built up around IBS-D. This is often where the most meaningful change in quality of life occurs, independent of any reduction in stool frequency itself. As the anticipatory anxiety eases, the nervous system has less fuel for the cycle that was sustaining the urgency in the first place.

What the Research Shows

Whorwell’s original trials and subsequent replications have consistently found significant improvement in bowel symptoms, abdominal pain, and quality of life following a course of gut-directed hypnotherapy, with Gonsalkorale and Whorwell’s long-term follow-up study finding that the majority of responders maintained improvement at five years. A 2016 randomised trial published in Alimentary Pharmacology & Therapeutics directly compared gut-directed hypnotherapy with the low-FODMAP diet and found comparable efficacy, with substantial proportions of participants in both arms reporting clinically meaningful improvement. More recent meta-analyses, including a 2024 systematic review, have confirmed that hypnotherapy produces durable symptom reduction across IBS subtypes, with effect sizes comparable to other first-line interventions and without the side-effect profile associated with antidiarrhoeal or antispasmodic medication.

What to Expect at London Hypnotics

I hold the HypnoIBS Diploma, a specialist qualification in gut-directed hypnotherapy, and my practice at 364 City Road, London EC1V 2PY, receives referrals from gastroenterology consultants at OneWelbeck and The London Clinic. IBS-D is a regular presentation in my clinical work, not a peripheral one.

The first session is a thorough clinical conversation. IBS-D varies considerably between individuals, and I want to understand your specific pattern: when symptoms began, what triggers urgency, how the anticipatory anxiety shows up in your daily life, what you have already tried, and how the condition has shaped your routines. I use an Ericksonian approach, indirect and collaborative rather than prescriptive, which tends to suit clients who are analytically minded or new to hypnotherapy.

Most clients complete a course of six to eight sessions, consistent with the evidence base. Sessions are available in person at 364 City Road, a short walk from Angel and Old Street stations, and online for those who prefer to work from home.

Frequently Asked Questions

Is hypnotherapy effective specifically for IBS-D, or only IBS in general? Research supports its effectiveness across IBS subtypes, including diarrhoea-predominant presentations. The mechanisms it addresses, sympathetic arousal, visceral hypersensitivity, and the anticipatory anxiety cycle, are present in IBS-D just as they are in IBS-C, though the specific suggestion and imagery work used in session is tailored to the subtype.

Do I need a diagnosis before starting hypnotherapy? Yes, ideally. If you have not had a structural cause ruled out by a GP or gastroenterologist, it is clinically sensible to do so first. I am always happy to liaise with treating clinicians where appropriate.

Can hypnotherapy work alongside the low-FODMAP diet? Yes. Many clients use both, and the research from Monash University found the two approaches produced comparable results independently, suggesting they may be complementary when used together rather than competing.

How long before I notice a difference? Most clients notice a reduction in general anxiety and nervous system arousal within the first few sessions, with changes in bowel pattern and urgency frequency typically developing across the middle of the course. You can read more about the related constipation-predominant subtype and IBS and SIBO on our blog.

Will I need to talk about embarrassing details? I understand this is often the hardest part of seeking help for IBS-D. In my experience, clients find the clinical conversation considerably less uncomfortable than they anticipated. This is a condition I treat regularly, and there is nothing you will describe that I have not heard before.

Taking the Next Step

Diarrhoea-predominant IBS is not something you have to keep managing quietly around the edges of your life. If dietary changes and medication have not resolved it, the explanation often lies in the gut-brain axis rather than in anything structurally wrong with your digestive system.

If you are in London or anywhere in the UK and would like to explore whether gut-directed hypnotherapy is right for you, I offer a free initial telephone consultation with no obligation to proceed.

You can reach me at 020 7101 3284 or book a free consultation via the link below.

Book Your Free Consultation


Antonios Koletsas is a GHSC-registered and GHR-accredited clinical hypnotherapist practising at 364 City Road, London EC1V 2PY. He holds the HypnoIBS Diploma and specialises in gut-directed hypnotherapy for IBS, functional gut disorders, and related gut-brain axis conditions. He is trained in Ericksonian Hypnotherapy at BHRTI under Stephen Brooks.

Clinical References

Gonsalkorale, W. M., & Whorwell, P. J. (2005). Hypnotherapy in the treatment of irritable bowel syndrome. European Journal of Gastroenterology and Hepatology, 17(1), 15–20.

Lacy, B. E., et al. (2021). ACG Clinical Guideline: Management of Irritable Bowel Syndrome. American Journal of Gastroenterology, 116(1), 17–44.

NICE (2017). Irritable bowel syndrome in adults: diagnosis and management. Clinical Guideline CG61. National Institute for Health and Care Excellence.

Peters, S. L., et al. (2016). Randomised clinical trial: the efficacy of gut-directed hypnotherapy is similar to that of the low FODMAP diet for irritable bowel syndrome. Alimentary Pharmacology & Therapeutics, 44(5), 447–459.

Whorwell, P. J., Prior, A., & Faragher, E. B. (1984). Controlled trial of hypnotherapy in the treatment of severe refractory irritable-bowel syndrome. Lancet, 2(8414), 1232–1234.

Lövdahl, J., et al. (2022). Gut-directed hypnotherapy in irritable bowel syndrome: a review of mechanisms and outcomes. Neurogastroenterology & Motility, 34(3), e14245.

gut-directed hypnotherapy
Health

Constipation and Gut-Directed Hypnotherapy: Why Your Gut Is Listening to Your Nervous System

Most people who come to me describing chronic constipation have already done the sensible things. They have adjusted their diet, increased fibre, reduced processed foods, tried magnesium supplements and probiotics. Some have been through several rounds of laxatives. A number have had colonoscopies that returned entirely normal results, which should have been reassuring, but in practice left them feeling more confused than before.

If the gut is structurally intact and the diet is reasonable, why isn’t it working?

The answer, in a growing number of cases, lies not in the bowel itself but in the relationship between the gut and the brain, and in the way the nervous system has learned to regulate, or more accurately to suppress, normal digestive movement. This is the clinical territory that gut-directed hypnotherapy is specifically designed to address, and it is why, for clients with chronic or functional constipation that has not responded to conventional approaches, it often produces results that those approaches could not.

This article explains what is actually happening when constipation becomes a persistent functional problem, why the nervous system is usually involved, and how gut-directed hypnotherapy at London Hypnotics approaches it.

IBS SIBO BRAIN AXIS

What We Mean by Functional Constipation

Constipation is one of the most common gastrointestinal complaints in the UK, affecting an estimated one in seven adults and disproportionately affecting women. In clinical terms, it is generally defined as fewer than three bowel movements per week, combined with one or more of the following: hard or lumpy stools, straining, a sensation of incomplete evacuation, or a sense of blockage.

There are constipation presentations with clear structural or pharmacological causes: thyroid disorders, certain medications, pelvic floor dysfunction, or anatomical abnormalities. These require their own clinical management and are not the primary focus here.

The more clinically complex group, and the one most relevant to this post, is functional constipation and the constipation-predominant subtype of irritable bowel syndrome (IBS-C). These presentations involve a demonstrably normal bowel on investigation, yet persistent and often debilitating symptoms. What they share is a disruption in the communication between the central nervous system and the enteric nervous system, the vast neural network that lines the gastrointestinal tract and governs its function.

This disruption is the mechanism that gut-directed hypnotherapy is designed to address.


The Gut-Brain Axis: Why Your Bowel Is Not Independent

The enteric nervous system contains approximately 500 million neurons and has long been informally described as the “second brain.” While it can operate with some degree of autonomy, it is in constant bidirectional communication with the central nervous system via the vagus nerve and the hypothalamic-pituitary-adrenal (HPA) axis.

This communication means that the state of the central nervous system, including its emotional tone, its stress load, and its level of arousal or suppression, has a direct and measurable impact on how the gut functions. The research in this area has developed substantially over the past two decades. We now understand that stress hormones, particularly cortisol and CRH (corticotropin-releasing hormone), directly affect gut motility, intestinal permeability, and the sensitivity of gut neurons to normal stimuli.

For constipation specifically, the relevant mechanism is this: sustained sympathetic nervous system activation, the physiological state associated with stress, anxiety, and chronic vigilance, actively suppresses intestinal motility. The digestive system is, in evolutionary terms, a non-essential function during threat response. Blood flow is redirected, muscular contractions slow, and the smooth muscle of the colon reduces its activity. The body is preparing to run or fight, not digest.

When that state becomes chronic rather than episodic, the suppression of gut motility can become entrenched. The nervous system is no longer responding to an acute stressor; it is simply operating at a baseline of elevated sympathetic tone. The colon continues to function sluggishly, not because anything is structurally wrong with it, but because the regulatory system governing its movement has become miscalibrated.

This is often the clinical picture I see in clients presenting with chronic constipation alongside anxiety, sleep difficulties, or a history of sustained stress: a nervous system that has been running at high arousal for so long that the digestive system’s normal rhythms have been persistently disrupted.


Why Dietary Changes Alone Often Fall Short

I want to be clear that dietary adjustment is not irrelevant. Adequate fibre, hydration, and reducing excess ultra-processed foods are clinically reasonable first steps and appropriate guidance from a GP or dietitian. The low-FODMAP diet has a meaningful evidence base for IBS presentations and can significantly reduce the fermentable substrates that contribute to bloating and discomfort in IBS-C.

But diet acts on the content and chemical environment of the bowel. It does not recalibrate the nervous system’s regulation of gut motility.

This is why many clients with functional constipation experience partial improvement on dietary changes and then plateau. They have optimised the inputs, but the underlying dysregulation of the gut-brain axis persists. The colon is still receiving the same dysregulated signals from a nervous system that has not been reset.

It is also worth noting that laxatives and stool softeners, while useful for short-term relief, do not address the neurological underpinnings of functional constipation. For many people, they become a long-term dependency rather than a curative intervention, because the mechanism generating the constipation remains unchanged.


The Psychological Dimension: What Constipation and Anxiety Share

There is a well-documented bidirectional relationship between constipation and psychological distress. Anxiety and chronic stress increase sympathetic nervous system dominance, which suppresses gut motility. Conversely, the experience of chronic constipation, the discomfort, the uncertainty, the disruption to daily life, generates its own anxiety and creates what clinicians recognise as a self-sustaining cycle.

Many clients with long-standing functional constipation have also developed a hypervigilant relationship with their body in relation to the bowel: monitoring closely for signs of movement, interpreting normal sensations with alarm, planning social and professional activities around toilet access, and carrying a low-level anticipatory dread of bad days. This hypervigilance is entirely understandable, but it maintains the elevated arousal state that suppresses the very function they are hoping to restore.

I see parallels here with other presentations where subconscious threat responses become embedded: panic attacks, sleep disorders, and stress-related pain syndromes. In each case, the nervous system is doing something it was designed to do, but in a context and at a frequency that was never intended.

The clinical insight that has made gut-directed hypnotherapy so effective for IBS and functional gut disorders is precisely this: if the nervous system is generating the problem, then working with the nervous system is the most direct route to resolution.


How Gut-Directed Hypnotherapy Works for Constipation

Gut-directed hypnotherapy was originally developed by Professor Peter Whorwell at the University of Manchester in the 1980s and has since accumulated one of the strongest evidence bases in the field of functional gastroenterology. It is now referenced in NICE guidance for IBS, and the Whorwell protocol is the benchmark against which newer approaches are measured.

The approach uses a focused state of deep relaxation, the hypnotic state, to access and influence the subconscious processes that regulate gut function. It is not simply relaxation, though relaxation is part of the mechanism. It is a therapeutic process that directly engages the gut-brain axis through a combination of physiological downregulation, targeted therapeutic suggestion, and imagery specifically designed to influence the enteric nervous system.

Here is how that process unfolds in a clinical context focused on constipation.

Recalibrating the Autonomic Nervous System

The hypnotic state is a potent activator of the parasympathetic nervous system, the physiological counterpart to the stress response. Research has documented measurable reductions in heart rate, respiratory rate, cortisol levels, and sympathetic nervous system activity during hypnosis. For a digestive system that has been operating under chronic sympathetic suppression, repeated access to deep parasympathetic activation begins to provide what dietary changes alone cannot: a genuine recalibration of the regulatory baseline.

As the nervous system’s resting tone shifts over the course of sessions, many clients notice that their digestive rhythm begins to normalise even before any specific gut-focused work has been completed. This reflects the direct impact of nervous system recalibration on colonic motility.

Direct Gut-Specific Therapeutic Suggestion

Within the hypnotic state, therapeutic suggestion is used to directly address the function of the gut. Drawing on the Whorwell protocol, this involves guided imagery and metaphor designed to influence the smooth muscle activity of the colon, the coordination of peristalsis, and the subconscious signals governing transit time.

Clients may be guided, for example, to visualise normal, comfortable gut movement, to develop a felt sense of ease and rhythm in the digestive system, or to update their relationship with gut sensations from one of alarm to one of trust and normalcy. These images and suggestions are not decorative. They are clinical tools that work on the enteric nervous system via the same pathways through which psychological stress disrupts it.

Reducing Visceral Hypersensitivity

Visceral hypersensitivity, an abnormally heightened sensitivity to gut sensations, is common in IBS-C and functional constipation. Clients often describe discomfort at levels of bowel distension that would not register as painful in the general population. This hypersensitivity is neurologically mediated and contributes significantly to the distress associated with the condition.

Gut-directed hypnotherapy has been shown in clinical research to reduce visceral hypersensitivity, particularly in IBS presentations. The mechanism involves both the direct neurological effect of the hypnotic state and the therapeutic reinterpretation of gut signals from threatening to neutral or informative. Over the course of treatment, clients typically find that gut sensations that previously triggered anxiety and avoidance become manageable and eventually unremarkable.

Addressing the Anxiety Around the Bowel

A meaningful part of the clinical work with constipation involves the psychological dimension specifically: the hypervigilance, the anticipatory anxiety, the planning and avoidance behaviours that have grown up around the condition. These maintain the elevated nervous system arousal that suppresses motility, and they erode quality of life independently of the physical symptoms.

Using Ericksonian techniques, we work within the hypnotic state to gently reduce the emotional significance the subconscious has attached to gut sensations and bowel function. This is not dismissing the client’s distress; it is working at the level where that distress is generated and maintained. Clients often describe a shift in their general relationship with their body in relation to the gut: from watchful and adversarial, to more trusting and settled.


What the Research Tells Us

The evidence base for gut-directed hypnotherapy in IBS and functional gut disorders is one of the most developed in the field of complementary and integrative medicine, and its application to constipation-predominant presentations specifically is well supported.

Whorwell and colleagues published the first randomised controlled trial of gut-directed hypnotherapy for IBS in 1984, with striking results. Subsequent trials have replicated these findings, with studies consistently reporting significant improvements in bowel frequency, stool consistency, abdominal pain, bloating, and psychological wellbeing following a standard course of gut-directed hypnotherapy.

A landmark study by Palsson et al. (2002), published in the American Journal of Gastroenterology, demonstrated significant improvements in global IBS symptoms, quality of life, and psychological distress in patients treated with a gut-directed hypnotherapy protocol, with effects maintained at twelve-month follow-up. The durability of treatment response is a particularly important finding, distinguishing gut-directed hypnotherapy from symptomatic interventions.

Research by Lea et al. (2003), published in Gut, found that gut-directed hypnotherapy produced significant improvement across all IBS subtypes, with constipation-predominant presentations showing particularly robust response in terms of bowel frequency and ease of defecation.

Gonsalkorale and Whorwell (2005) reviewed the long-term outcomes of over 200 IBS patients treated with gut-directed hypnotherapy and found that 83% of patients who had responded to treatment maintained their improvement at follow-up periods of up to five years. This level of long-term durability is unusual in the management of functional gut disorders.

More recently, a systematic review by Lee et al. (2014) confirmed that gut-directed hypnotherapy produces significant reductions in IBS symptom severity scores, comparable in magnitude to other established pharmacological and psychological interventions, with the additional advantage of sustained response without the side effect profile associated with medication.

These findings inform my clinical approach and my confidence in recommending gut-directed hypnotherapy as a primary intervention for clients with IBS-C and functional constipation who have not found adequate resolution through conventional means.


What to Expect at London Hypnotics

I hold a specialist qualification in gut-directed hypnotherapy through the HypnoIBS Diploma, which focuses specifically on treating IBS and functional gastrointestinal conditions. My practice at 364 City Road, London EC1V 2PY, receives referrals from gastroenterology consultants at OneWelbeck and The London Clinic, and this specialist focus means that gut presentations are not a peripheral part of what I do but a clinical area I work in regularly.

The first session begins with a thorough clinical conversation. Constipation and IBS-C present differently for every person, and I want to understand yours specifically: when symptoms began, what your bowel pattern typically looks like, whether stress or anxiety has been a feature, what dietary and medical approaches you have tried, and how the condition has affected your daily life. This understanding shapes the therapeutic plan.

I use an Ericksonian approach alongside the Whorwell-based protocol: indirect, permissive, and tailored to you as an individual rather than applied as a generic script. For clients who are sceptical about complementary approaches, or who have not previously encountered hypnotherapy, this approach tends to feel more collaborative and less prescriptive than they anticipated.

For IBS-C and functional constipation, most clients complete a course of six to eight sessions, consistent with the evidence base. Changes in bowel frequency and general digestive ease often become apparent across the middle sessions, with consolidation and reduction in anxiety around the gut continuing through the latter part of the course. Sessions are available in person at 364 City Road, a short walk from Angel and Old Street stations, and online for clients who prefer to work from home.


Frequently Asked Questions

Is gut-directed hypnotherapy evidence-based? Yes. Gut-directed hypnotherapy is referenced in NICE guidance for IBS and has one of the most robust evidence bases of any psychological intervention for functional gut disorders. The Whorwell protocol, developed at the University of Manchester, has been evaluated in multiple randomised controlled trials over four decades, with consistently positive outcomes for IBS-C and related presentations.

Can gut-directed hypnotherapy help if I have been diagnosed with IBS-C rather than just constipation? Yes. IBS-C is one of the primary presentations for which gut-directed hypnotherapy was originally developed and validated. The protocol addresses the full cluster of IBS-C symptoms: bowel frequency, stool consistency, abdominal discomfort, bloating, and the anxiety that often accompanies the condition. Research specifically on IBS-C subtypes supports robust and durable response.

Do I need a GP referral? No, though I always recommend informing your GP that you are pursuing gut-directed hypnotherapy, and I am always willing to liaise with treating clinicians where appropriate. If you have not had a medical investigation of your constipation and have not been formally assessed by a doctor, it is clinically sensible to ensure a structural or medical cause has been ruled out before pursuing hypnotherapy specifically.

How is this different from just relaxation? Relaxation is a component of the mechanism, but gut-directed hypnotherapy is considerably more targeted than general relaxation. Within the hypnotic state, specific therapeutic suggestions, imagery, and interventions are directed at the gut-brain axis and at the function of the colon specifically. This targeted work is what produces the clinical results documented in the research literature. A relaxation recording does not do the same thing.

What if I have constipation alongside other IBS symptoms? This is the most common clinical picture. IBS rarely presents as a single symptom, and constipation in IBS-C is usually accompanied by bloating, cramping, incomplete evacuation, and variability in symptoms across days. The gut-directed hypnotherapy protocol is designed for this full symptom picture. You can read more about IBS presentations and gut-directed hypnotherapy in the related posts on IBS and SIBO and gut-directed hypnotherapy in London.

Can hypnotherapy help with the anxiety that has built up around my gut symptoms? Yes, and addressing this is a central part of the clinical work. The anxiety that develops around gut symptoms, the monitoring, the anticipatory dread, the social and professional planning around bowel access, contributes directly to maintaining the nervous system dysregulation that suppresses motility. Reducing that anxiety is not simply a quality-of-life benefit; it is a core component of restoring normal gut function.


Taking the Next Step

Chronic constipation that has not responded to dietary or pharmacological approaches is not a sign that nothing more can be done. For many people, it is a sign that the approach has been focused on the wrong level. The gut-brain axis is where the problem lives, and it is where the most effective solutions tend to be found.

If you are in London or anywhere in the UK and would like to explore whether gut-directed hypnotherapy is the right approach for you, I offer a free initial telephone consultation. There is no obligation and no pressure to proceed.

You can reach me at 020 7101 3284 or book a free consultation via the link below.

Book Your Free Consultation


Antonios Koletsas is a GHSC-registered and GHR-accredited clinical hypnotherapist practising at 364 City Road, London EC1V 2PY. He holds the HypnoIBS Diploma and specialises in gut-directed hypnotherapy for IBS, functional constipation, and related gut-brain axis conditions. He is trained in Ericksonian Hypnotherapy at BHRTI under Stephen Brooks.

Clinical References

Gonsalkorale, W. M., & Whorwell, P. J. (2005). Hypnotherapy in the treatment of irritable bowel syndrome. European Journal of Gastroenterology and Hepatology, 17(1), 15–20.

Lea, R., Houghton, L. A., Calvert, E. L., Larder, S., H077, N. W., Whorwell, P. J., & Bankart, J. (2003). Gut-focused hypnotherapy normalises disordered rectal sensitivity in patients with irritable bowel syndrome. Alimentary Pharmacology and Therapeutics, 17(5), 635–642.

Lee, H. H., Choi, Y. Y., & Choi, M. G. (2014). The efficacy of hypnotherapy in the treatment of irritable bowel syndrome: a systematic review and meta-analysis. Journal of Neurogastroenterology and Motility, 20(2), 152–162.

NICE (2017). Irritable bowel syndrome in adults: diagnosis and management. Clinical Guideline CG61. National Institute for Health and Care Excellence.

Palsson, O. S., Turner, M. J., Johnson, D. A., Burnett, C. K., & Whitehead, W. E. (2002). Hypnosis treatment for severe irritable bowel syndrome: investigation of mechanism and effects on symptoms. Digestive Diseases and Sciences, 47(11), 2605–2614.

Whorwell, P. J., Prior, A., & Faragher, E. B. (1984). Controlled trial of hypnotherapy in the treatment of severe refractory irritable-bowel syndrome. Lancet, 2(8414), 1232–1234.

Stressed woman holing her head
Health

Hypnotherapy for Panic Attacks in London: Why the Pattern Persists and How to Break It at the Source

There is a particular quality to a first panic attack that almost everyone who has experienced one describes in the same way. It arrives without warning. It convinces the person, absolutely and physically, that something catastrophic is happening. And then it passes, leaving behind something that in many ways is more consequential than the attack itself: a nervous system that now knows this is possible.

That residue is what I want to talk about in this article, because it is the real clinical problem with panic attacks, and it is the piece that most short-term interventions fail to address.

The panic attack itself lasts minutes. The pattern it installs can persist for years.

If you are reading this as someone who has experienced panic attacks, whether once, occasionally, or with a frequency that has begun to shape how you live your life, this article is intended to help you understand what is actually happening and why hypnotherapy addresses it at a level that other approaches often cannot reach.

Stressed woman holing her head

What a Panic Attack Actually Is

A panic attack is an acute activation of the sympathetic nervous system in the absence of genuine threat. In neurological terms, the amygdala, the brain’s threat-detection centre, fires as though a life-threatening danger is present. The body responds accordingly: heart rate surges, breathing becomes shallow and rapid, blood is redirected away from the digestive system and toward the large muscles, adrenaline floods the system. Every physiological event occurring in a panic attack is the body preparing, with great efficiency, to run or fight.

The problem is that there is nothing to run from.

This is not a malfunction. The amygdala is doing precisely what it is designed to do. The issue is that it has become miscalibrated, responding to cues, whether internal sensations, particular environments, specific thoughts, or more diffuse states, as though they signal danger when they do not.

Common presentations I see in my practice include panic attacks triggered by: crowded public spaces or the London Underground, physical sensations such as a slightly elevated heart rate or mild dizziness, social or professional situations involving scrutiny, or what seems like no external trigger at all, occurring at rest or even during sleep. The content of the trigger varies. The underlying mechanism is consistent.

It is worth being clear about the physiology involved, because understanding it matters clinically. During a panic attack, hyperventilation is common. Breathing rapidly and shallowly reduces carbon dioxide in the bloodstream, which changes blood pH and causes the tingling in the hands, the light-headedness, and the feeling of unreality that many people describe. These sensations are real and uncomfortable, but they are not dangerous. The body is not failing. It is responding to a perceived threat that the conscious mind cannot verify but the subconscious insists is present.


Why the Pattern Persists: The Fear of Fear

The first panic attack is frightening. What makes panic disorder a clinical condition rather than an isolated episode is what happens in the aftermath.

The experience of a panic attack is sufficiently alarming that the nervous system files it as evidence of genuine danger. Not the danger of a single moment, but a category of danger: that certain internal states, certain places, certain circumstances, can produce catastrophe. The subconscious begins to scan constantly for those cues. This hypervigilance is well-intentioned. Its function is to detect the danger early so it can be avoided.

But the vigilance itself generates the physiological arousal it is trying to detect. A slightly faster heartbeat, noticed and interpreted as threatening, triggers anxiety. That anxiety raises the heart rate further. The catastrophic interpretation intensifies. The alarm system, monitoring for signs of a panic attack, finds exactly what it is looking for and treats the finding as confirmation. The attack arrives.

This is the central paradox of panic disorder: the attempt to prevent panic creates the conditions for it. Clinical researchers refer to this as the fear-of-fear cycle, and it is the mechanism by which a single frightening event can become a self-sustaining pattern that persists long after any original stressor has resolved.

This cycle tends to produce a second layer of consequences that are often as limiting as the panic attacks themselves. Avoidance develops. Certain places are no longer visited. Certain situations are restructured around. Physical exercise is reduced because it raises the heart rate. Alcohol is used to lower arousal, then rebound anxiety worsens the problem. Life begins to contract.

In London, this contraction carries particular costs. The Underground becomes inaccessible. Networking events, client meetings, professional environments with high social density, these become sites of anticipatory dread. I see clients at my Clerkenwell practice who are managing demanding professional lives while quietly organising their daily existence around the avoidance of situations that might trigger a panic attack. The energy this requires is considerable. The erosion to quality of life, over time, is significant.


Why Reassurance and Breathing Techniques Are Not Enough

There are a number of widely recommended approaches to managing panic attacks, and I want to be fair about their value before explaining why they are often insufficient on their own.

Controlled breathing, particularly techniques that lengthen the exhale and reduce hyperventilation, can meaningfully interrupt the physiological escalation of an acute attack. Extended exhale breathing activates the vagus nerve and begins to engage the parasympathetic nervous system. This is real and useful.

Psychoeducation about the nature of panic, the understanding that the physical sensations are not dangerous and cannot cause harm, is also clinically valuable. Many people find that knowing the dizziness and racing heart are caused by hyperventilation rather than cardiac pathology reduces the secondary layer of fear significantly.

Cognitive Behavioural Therapy has a well-established evidence base for panic disorder, and for many people it provides meaningful reduction in both frequency and intensity of attacks.

But in clinical practice, a meaningful proportion of people who understand panic attacks intellectually, who can explain exactly what is happening physiologically, who have practised breathing techniques and completed CBT protocols, continue to experience them. They are not failing the treatment. The pattern is simply not living where those approaches reach.

Panic attacks originate in the amygdala, a structure that operates subcortically, below the level of conscious cognition. The amygdala responds to threat faster than the prefrontal cortex can formulate a reassuring thought. The body is already in the alarm state before any rational appraisal has had the opportunity to engage. Telling yourself during a panic attack that your heart is fine is not ineffective because it is incorrect. It is limited in effect because it is arriving at the wrong level.

To change the pattern at its root, it is generally necessary to work at the level where the root is located.


The Subconscious Architecture of Panic

When I work with clients presenting with panic attacks, one of the most consistent clinical observations is that the pattern rarely originates with the first attack. The first attack is usually a crystallisation of something that has been developing for longer.

In most cases, there is a preceding period of sustained stress, emotional suppression, or accumulated anxiety that has been managed, reasonably successfully, for some time. The nervous system has been carrying more than it was designed to carry. The first panic attack is often less a sudden breakdown than a system that has finally exceeded its load-bearing capacity.

What the subconscious does with that event is the clinically significant part. It encodes it as evidence of a specific vulnerability, a specific kind of danger. It then constructs a surveillance programme around that evidence. It adjusts the interpretation of ambiguous bodily sensations accordingly. It begins associating certain environments and situations with threat. None of this happens consciously. It happens in the same place where habits are formed, where conditioned responses live, where the automatic patterns that govern the vast majority of daily behaviour are stored.

This is why hypnotherapy is particularly well-suited to panic. It creates direct, focused access to exactly those subconscious processes, in a state where they are more receptive to revision than they are during ordinary waking consciousness.


How Hypnotherapy Works for Panic Attacks

Recalibrating the Nervous System’s Baseline

The hypnotic state is a potent and measurable activator of the parasympathetic nervous system. Research has documented significant reductions in heart rate, breathing rate, cortisol levels, and sympathetic nervous system activity during hypnosis. For someone whose autonomic nervous system has been locked in a state of chronic sympathetic dominance, the regular experience of deep hypnotic relaxation begins to genuinely recalibrate the baseline.

This is not simply a pleasant experience of relaxation, though it is that as well. It is a physiological recalibration. The nervous system, through repeated access to this state, relearns that deep downregulation is possible and safe. The floor of background arousal begins to lower. The threshold between ordinary alertness and alarm increases. Panic attacks, which require a certain level of background tension to ignite, become less likely as that background level comes down.

Many clients notice, within the first few sessions, that their general anxiety level has reduced even before we have done any specific work on the panic pattern itself. This is the recalibration effect, and it matters because it makes the subsequent, more specific work considerably more accessible.

Identifying and Updating the Subconscious Trigger

Using Ericksonian techniques, we work within the hypnotic state to identify the specific subconscious associations that are driving the panic pattern. This often involves exploring the circumstances of the first attack and the period preceding it, not to relive the experience, but to understand, with the perspective and resources of an adult, the context in which the nervous system made its conclusions.

The subconscious mind, in the receptive state of hypnosis, can be introduced to a genuinely revised interpretation of those events. Rather than: “certain internal sensations signal catastrophic danger”, the nervous system begins to build associations with the alternative: that those sensations are manageable, familiar, temporary, and not threatening. Rather than: “certain environments are unsafe”, the subconscious begins to accumulate evidence that they have been navigated without harm.

This is not cognitive reframing at the conscious level. It is working directly with the mechanism that generates the alarm response, in the state where that mechanism is most accessible.

Interrupting the Anticipatory Anxiety Cycle

A significant portion of the clinical work with panic involves the anticipatory anxiety that has developed around the attacks themselves. The dread of the next attack, the constant bodily monitoring, the hypervigilance toward internal sensations, these maintain the elevated baseline that makes further attacks more likely. Addressing the attacks alone, without addressing the fear-of-fear cycle, often produces incomplete resolution.

In hypnotherapy, we work specifically on the anticipatory response: reducing the interpretive significance of ambiguous bodily sensations, diminishing the hypervigilance, and rebuilding a relationship with the body in which its signals are experienced as informative rather than threatening. Clients learn, at the subconscious level, to respond to a slightly elevated heart rate with curiosity rather than alarm. The cycle that sustained the pattern begins to lose its fuel.

Building Genuine Inner Safety

The experience of repeated panic attacks tends to erode something that might be called a basic sense of bodily safety. The body has become a source of alarming surprises. Many clients describe a pervasive low-level vigilance toward their own physical state, a kind of watchfulness that was not there before.

A central part of the hypnotherapy work involves rebuilding a felt sense of safety and competence in relation to the body and to challenging situations. Through guided imagery and inner resource-building techniques, clients develop an experiential sense of being able to manage difficult states, not by avoiding them, but by moving through them without catastrophe. This competence, once accessed repeatedly in the hypnotic state, begins to transfer to real-world experience.


Panic Attacks and Sleep: An Important Connection

It is worth noting the relationship between panic attacks and sleep, because the two are clinically intertwined in ways that are often overlooked.

Nocturnal panic attacks, attacks that occur during sleep and wake the person suddenly in a state of full sympathetic arousal, are more common than is widely appreciated. They typically occur during the transition between sleep stages rather than during dreaming, and they represent the same dysregulated alarm response operating without the involvement of any conscious trigger.

More broadly, the chronic hyperarousal that maintains a panic disorder pattern tends to produce significant sleep disruption: difficulty falling asleep due to heightened bodily vigilance, early morning waking, and non-restorative sleep. Poor sleep, in turn, lowers the threshold for panic, creating a reinforcing cycle. Hypnotherapy’s capacity to work simultaneously on both the panic pattern and the sleep disruption is clinically useful, and many clients find that improvements in one domain begin to support improvements in the other.


Panic Attacks and the London Context

I want to address the specific context of living and working in London, because it matters clinically.

London is a city of relentless sensory and social intensity. The Underground alone, with its heat, density, and the particular social pressure of close proximity to strangers in enclosed spaces, is a significant trigger for many people with panic disorder. The professional culture here is demanding and public in ways that create particular vulnerability for anyone already monitoring themselves for signs of losing control.

The social cost of panic attacks in London is also high. The city’s density means that avoidance strategies are constantly tested. You cannot easily avoid crowds, enclosed spaces, or high-pressure public situations if you work in central London. What might be a manageable limitation in other environments becomes a significant daily negotiation here.

This is one reason why I see such a range of people presenting with panic attacks: professionals who are otherwise high-functioning, people who have been managing the pattern quietly for years without discussing it, and people who have reached a point where the contraction of their life has become no longer acceptable. The common thread is that the pattern has persisted beyond what anyone should have to accommodate as a normal feature of their life.

Panic disorder is highly treatable. That is not a reassuring platitude. It is a clinical fact.


What Does the Research Say?

The evidence base for hypnotherapy in anxiety disorders, including panic, is well developed and growing. A meta-analysis by Milling et al. (2018), published in the International Journal of Clinical and Experimental Hypnosis, found robust support for hypnotherapy as an intervention for anxiety across a range of presentations, with effect sizes comparable to other evidence-based treatments.

Research by Kirsch, Montgomery and Sapirstein (1995) demonstrated that adding hypnosis to cognitive-behavioural approaches produced significantly superior outcomes compared to CBT alone across anxiety presentations. Given that CBT is the primary evidence-based treatment for panic disorder, this finding is directly relevant.

Neuroimaging work by Deeley and colleagues at King’s College London documented measurable changes in prefrontal cortex and anterior cingulate activity during hypnosis, regions that are directly implicated in the emotional regulation deficits seen in panic disorder. The hypnotic state appears to modulate activity in precisely the brain areas that panic disorder dysregulates.

Research by Alladin (2012) on cognitive hypnotherapy specifically supports the value of integrating hypnotic techniques with psychotherapeutic work for anxiety presentations, and reports that gains made through hypnotherapy tend to be durable at follow-up, a clinically important finding for a condition that can be prone to relapse with symptom-focused approaches.


What to Expect at London Hypnotics

The first session always begins with a full clinical conversation. Panic disorder has a different clinical profile for every person who experiences it, and I want to understand yours specifically: when the first attack occurred, what the circumstances were, which situations you have begun to avoid, how your sleep and daily functioning have been affected, and what you have tried previously.

I use an Ericksonian approach throughout: indirect, permissive, and built around you as an individual rather than a protocol applied generically. This approach is particularly effective for clients who are analytically minded or who have reservations about more directive methods, a description that fits many of the professionals I see.

For panic disorder, most clients find meaningful change across four to six sessions, with nervous system recalibration and reduction in anticipatory anxiety often developing early in the process and the deeper pattern work consolidating across the course of treatment. Some clients with more longstanding or complex presentations benefit from a slightly extended course.

Sessions are available in person at 364 City Road, London EC1V 2PY, a short walk from Angel and Old Street stations, and online for clients who prefer to work from home or who are based outside central London.


Taking the Next Step

Panic attacks are not a character flaw, and they are not a permanent feature of your neurology. They are a pattern, and patterns can change. If what you have read here resonates with your experience, I would welcome the opportunity to speak with you.

You can reach me at 020 7101 3284 or book a free consultation via the link below.

Book Your Free Consultation


Antonios Koletsas is a GHSC-registered and GHR-accredited clinical hypnotherapist practising at 364 City Road, London EC1V 2PY. He specialises in anxiety, panic disorder, insomnia, IBS, and trauma-related presentations, and is trained in Ericksonian Hypnotherapy at BHRTI under Stephen Brooks.

Clinical References

Alladin, A. (2012). Cognitive hypnotherapy for major depressive disorder. American Journal of Clinical Hypnosis, 54(4), 275–293.

Deeley, Q. et al. (2012). Modulating the default mode network using hypnosis. International Journal of Clinical and Experimental Hypnosis, 60(2), 206–228.

Kirsch, I., Montgomery, G., & Sapirstein, G. (1995). Hypnosis as an adjunct to cognitive-behavioral psychotherapy. Journal of Consulting and Clinical Psychology, 63(2), 214–220.

Milling, L. S., Valentiner, D. P., & Alladin, A. (2018). The efficacy of hypnosis as an intervention for anxiety: a meta-analytic review. International Journal of Clinical and Experimental Hypnosis, 66(4), 336–363.

NICE (2011). Generalised anxiety disorder and panic disorder in adults: management. Clinical Guideline CG113. National Institute for Health and Care Excellence.

1 2 3 4 5
Privacy Settings
We use cookies to enhance your experience while using our website. If you are using our Services via a browser you can restrict, block or remove cookies through your web browser settings. We also use content and scripts from third parties that may use tracking technologies. You can selectively provide your consent below to allow such third party embeds. For complete information about the cookies we use, data we collect and how we process them, please check our Privacy Policy
Youtube
Consent to display content from - Youtube
Vimeo
Consent to display content from - Vimeo
Google Maps
Consent to display content from - Google
Spotify
Consent to display content from - Spotify
Sound Cloud
Consent to display content from - Sound